
Top

Early Career Awardees

Using AI and Brain Imaging to Understand Psychosis Across Brain Disorders

Linda Bryant

Linda Bryant

What drew me to psychosis research

Psychosis is not limited to one diagnosis. It can occur in schizophrenia, but also in neurological conditions such as Parkinson's disease and behavioural variant frontotemporal dementia (bvFTD). I became interested in psychosis research through my clinical work in an NHS Early Intervention in Psychosis service. This experience highlighted the clinical complexity of psychosis and the substantial variation in its presentation between individuals. It also underscored how much remains to be understood about why psychosis emerges across different brain disorders and what underlies this individual variation.

This led me to ask whether psychosis is associated with shared brain features across diagnoses or whether it emerges through different pathways in different conditions. Answering this is difficult because brain imaging produces large and complex datasets, and the most informative patterns may be subtle and spread across many regions. Artificial intelligence (AI) offers a way to bring these patterns together and examine how they differ between individuals. This interest now forms the basis of my PhD at King's College London, where I use AI and brain imaging to study psychosis across psychiatric and neurodegenerative conditions, with the aim of supporting more personalised care.

My research at and since the SIRS Congress

At SIRS 2026, I presented research examining the brain features associated with psychosis in Parkinson's disease. Although Parkinson's is usually known for its movement symptoms, more than half of people may experience psychosis over the course of the illness, often as visual hallucinations or delusions. This is associated with faster cognitive decline, a greater risk of dementia, increased pressure on caregivers and earlier admission to residential care. Clinicians, however, still have limited tools for identifying who is most at risk.

We analysed structural MRI scans from 481 people with Parkinson's disease, including 135 who had experienced psychosis. Using machine learning, we found that patterns across visual, motor and deeper dopamine-related brain systems could distinguish those who had experienced psychosis better than chance. Visual-processing regions were particularly informative, which is especially relevant because visual hallucinations are a prominent feature of Parkinson's psychosis. This work is a first step towards moving from average group differences to information that may eventually be useful for an individual person.

My wider research also examines the boundary between schizophrenia and neurodegeneration. In a recent study, we found preliminary evidence that some people with schizophrenia express a brain pattern associated with lower dopamine production and higher iron levels in a deep brain region called the striatum. This pattern resembles changes seen in behavioural variant frontotemporal dementia (bvFTD), suggesting that a subgroup of people with schizophrenia may show neurodegeneration-like features. These findings may help us better understand the biological heterogeneity within schizophrenia.

Why SIRS matters

SIRS provides a valuable forum for exchanging ideas with researchers and clinicians who approach psychosis from different perspectives. Receiving an Early Career Award made the Congress especially rewarding, as it offered a fantastic opportunity to connect with other awardees, follow their research beyond the meeting and benefit from mentorship within the SIRS community.

Where I want to take the research next

In the future, I want to continue using AI to advance precision medicine across psychosis and neurodegenerative conditions. I plan to continue combining brain imaging with clinical information to better predict individual risk and treatment outcomes. The longer-term aim is to translate these tools into clinical workflows, so that information from each person can guide earlier and more precise decisions about monitoring and treatment. Ultimately, I hope this work helps move care away from one-size-fits-all approaches and towards support that is tailored to the individual.

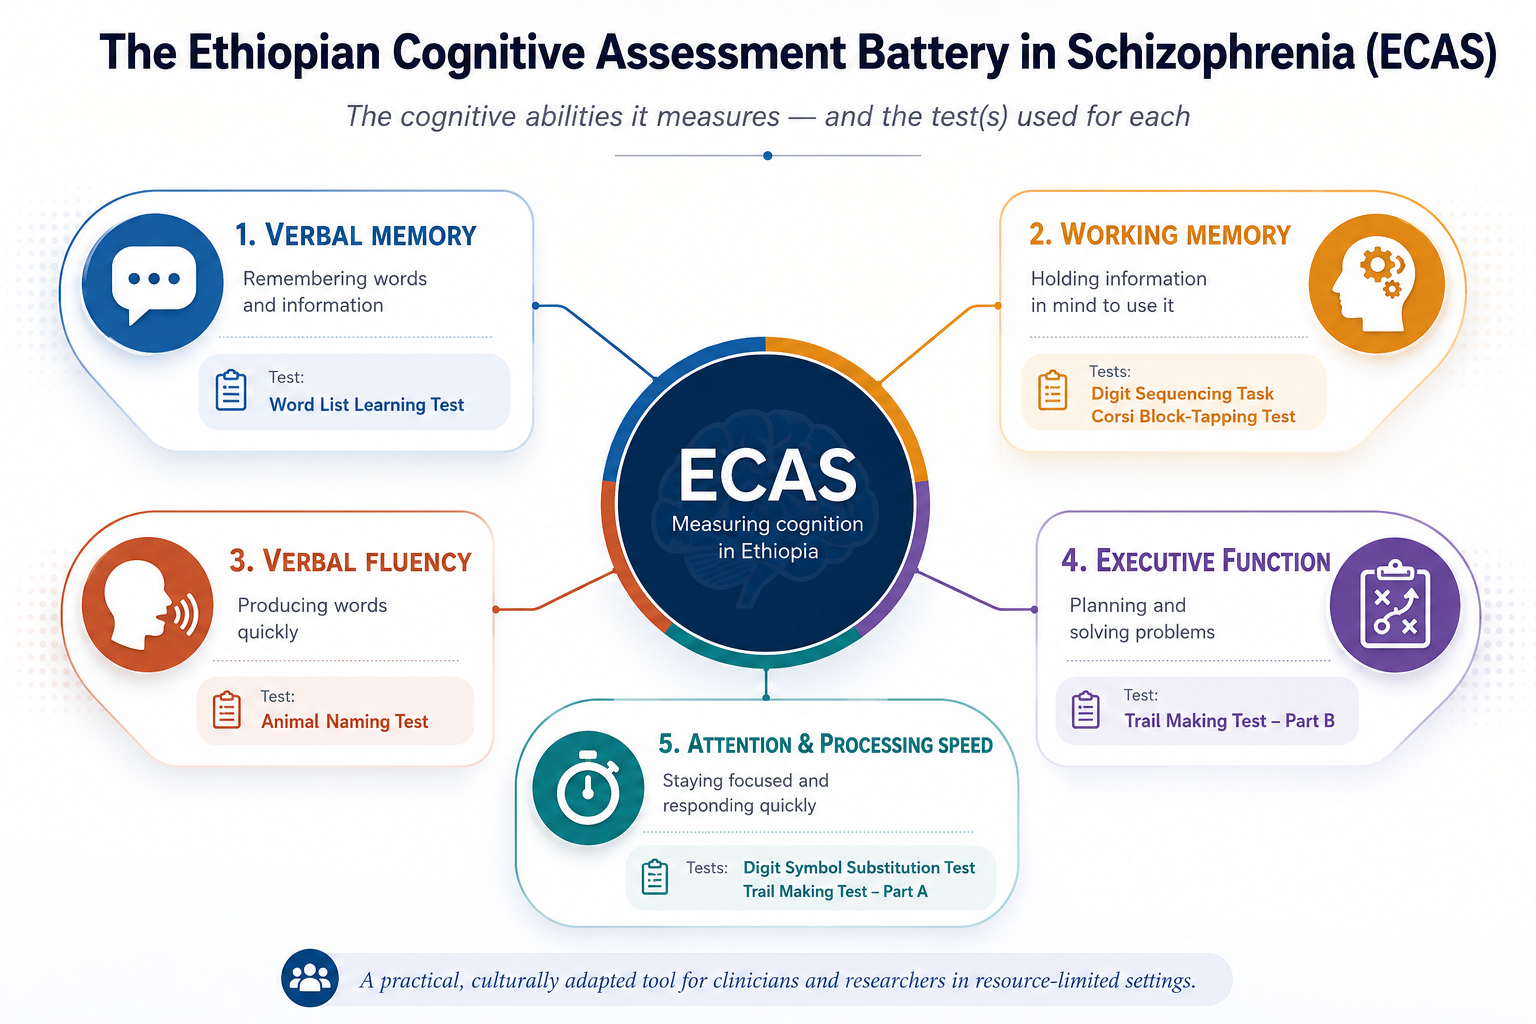
Assessing Cognition in People with Schizophrenia in Resource-Limited Settings

Early in my career, I worked as a mental health professional in Ethiopia, spending time with people living with schizophrenia and with their families. One thing stayed with me from this experience: the part of the illness that often shaped their lives went mostly unnoticed: cognitive difficulties. These difficulties influence whether they can go to school, hold a job, run a household, or simply keep up with a conversation. Yet they were rarely talked about, rarely measured, and almost never treated. This gap is what drew me into schizophrenia and psychosis research.

To me, one of the most important questions in our field is: how do we recognise and respond to cognitive difficulties in people with schizophrenia? Studies have shown that cognitive remediation therapies can improve these impairments. But before we can offer any treatment, we must be able to measure cognition. In a country like Ethiopia, where specialist clinicians are scarce and there are no validated tools, even this first step was a challenge.

This became the focus of my PhD at Addis Ababa University, supported by the African Mental Health Research Initiative (AMARI). My aim was to develop a measure of cognition that was not only valid, but feasible and acceptable for mental health professionals working in Ethiopian settings. Measuring cognition matters because it lets us track how an illness changes over time, judge whether a treatment is working, and match each person to the best rehabilitation pathway.

Building such a tool in a resource-limited setting is harder than it sounds. There are few clinicians, little time to administer long assessments, expensive, and limited awareness of cognitive difficulties in the first place. Tools developed in higher-income countries cannot simply be translated and reused, as language and culture pose barriers. When adapting a memory test that uses word lists, for instance, the words have to reflect things that are genuinely part of people’s daily lives. So, I reviewed the existing literature, identified the most promising tools, and then consulted at length with local clinicians, people with lived experience, research experts and family members. Those conversations let me to select, adapt and refine a set of measures, which became the Ethiopian Cognitive Assessment Battery in Schizophrenia (ECAS), a battery assessing six domains of cognition (verbal memory, working memory, verbal fluency, attention and processing speed, and executive function) that clinicians and researchers in Ethiopia can now use. With my supervisors’ support. I led the development and validation of this measure, which was published in six papers listed below.

Being part of the SIRS community has shaped this journey more than I expected. Presenting at the Congress and receiving a SIRS Early Career Award gave me the opportunity to connect with researchers from around the world working on the same questions and to give my work the visibility it could never have achieved from Ethiopia alone. For an early-career researcher from a low-income setting, that recognition is not just encouraging; it also opens doors, builds collaborations, and signals that this kind of work belongs in the global conversation about psychosis. SIRS matters for people with psychosis precisely because it keeps making that conversation more global and moving beyond the few well-resourced settings where most research is still done.

Where do I want to take this next? My current postdoctoral work, again supported by the Wellcome Trust–funded AMARI network, focuses on closing the literacy gap in cognitive assessment by adapting and norming versions of ECAS so they work even for people with little or no formal education, a reality for many in low-income settings. Looking further ahead, I think about a young person who develops psychosis a few years from now in rural Ethiopia. My hope is that, by then, recognising and addressing their cognitive difficulties will be a routine part of their care, not a privilege reserved for those who happen to live near a specialist centre.

It has been an incredible journey, and there is still a great deal to do across Africa and other low-income settings to improve the prospects of people living with a schizophrenia diagnosis. If you have an interest, skills or expertise to share, do get involved. There is much to give and much more to gain.


Early Career Awardee – Bridget King

Early Career Awardee Banner

Bridget King

Transcript:

My name is Bridget King, and I will have a poster at SIRS 2025 which is presenting a mega-analysis looking at neurometabolite levels in antipsychotic responsive versus non-responsive psychosis. It is estimated that up to 30% of patients with schizophrenia will not respond to antipsychotic medication. Research using a brain imaging method called magnetic resonance spectroscopy or MRS has linked elevations in glutamate in the medial frontal cortex to non-response to antipsychotics. However, not all studies in this field have found elevations in glutamate in antipsychotic non-responders, and some studies have linked additional neurometabolites in this process, such as choline and myo-inositol. Patients with schizophrenia that don't respond to their antipsychotic medication have a higher illness burden because they have persistent symptoms of the disorder. Understanding the neurobiological mechanisms as to why some individuals with schizophrenia don't respond to antipsychotics could help pave the way to develop new and more effective treatments for schizophrenia. For example, if non-response to psychosis is associated with elevations in glutamate, these individuals may benefit from glutamatergic acting therapeutics.


My poster at SIRS 2025 presents a large-scale collaborative mega-analysis, which combines MRS data from 19 studies and over 1,000 participants from around the globe. This research aims to answer critical questions in the field, such as whether elevations in neurometabolites such as glutamate are linked to non-response in schizophrenia. If you would like to find out more about this research and our findings, please come along and visit my SIRS poster on April 1st at the Riverside Exhibit Hall West. It's poster number 102, and it's happening from 12 until 2 p.m.


Early Career Awardee – Anne Felsenheimer

Early Career Awardee Banner

Anne Felsenheimer

Transcript:

Hi, I’m Anne Felsenheimer — a medical doctor and PhD at the Institute of Cognitive Neuroscience at UCL and the Max Planck Institute of Cognitive and Behavioural Brain Sciences. 

At this year’s Congress of the Schizophrenia International Research Society, I’m presenting my work on interoception and the feeling of presence, conducted in collaboration with Sohee Park’s Lab during my time as an International Fulbright Scholar.  

Sometimes we're just sitting in a room, maybe working on the next presentation... 

... and suddenly we get this strange feeling that there is someone else in the room with us.  

We might even turn around and realise that no, actually we are still alone. This feeling of someone being there when they are not called felt presence. Why do we have this feeling?  


One idea is, that we indeed sense something that is there - such as our heartbeat. 

But instead of attributing it to our own body, we think this sensation is coming from someone else.  

Although there is a lot of stigma attached to it, the feeling of presence is actually quite common. It's not always unsettling - sometimes it can feel like a comforting presence, even like a guardian angel. But it is also associated with a higher risk of psychosis, where the felt presence is often more distressing. One might ask: are there different mechanisms at work?  

By studying felt presence, we can gain new insights of how perception and consciousness works on a general level. 

But this research also helps us distinguish between harmless and potentially high-risk experiences, develop targeted interventions and reduce the stigma surrounding these mysterious sensations. 

Early Career Awardee – Huiquan Zhou

Early Career Awardee Banner

Huiquan Zhou

Slide 1 

Hi, everyone. Thank you for being here today. I am excited to present our study on the association between clozapine use and the risk of hospitalization among people with schizophrenia, using a self-controlled case series study design. 

Slide 2 

Schizophrenia is a chronic and severe mental disorder that often leads to recurrent hospitalizations, placing a significant burden on patients, families, and healthcare systems. Clozapine, the gold-standard treatment for TRS, has been shown to reduce symptoms and improve outcomes. However, critical gaps remain in our understanding of its real-world impact on hospitalization risk. 

First, there is limited evidence of clozapine’s impact on specific types of hospitalizations, such as psychiatric versus non-psychiatric admissions. Second, the comparative effectiveness of clozapine versus depot in preventing hospitalizations remains controversial, with conflicting findings in the literature. Third, real-world evidence is limited, and previous cohort studies often fail to address confounding due to between-person comparisons. 

To address these gaps, we conducted a self-controlled case series study, a robust method where each individual serves as their own control. This design divides the observation period for each individual into different exposure types, eliminating the influence of fixed confounders such as genetics or chronic comorbidities. Our study leverages a regional representative cohort of new clozapine users in Hong Kong, providing a unique opportunity to examine clozapine’s real-world effectiveness under the Chinese context. 

Slide 3 

We first compare the effectiveness of clozapine with other antipsychotics in general. We divided the observation periods into the pre-exposure period, the first clozapine exposure period, the washout period, the subsequent clozapine exposure period, and the period using other antipsychotics. We found that, compared to the use of other antipsychotics, both the first clozapine use and subsequent clozapine use showed significant lower risk associated with all-cause, psychiatric and non-psychiatric hospitalization.    

Slide 4 

We then compare the effectiveness of depot and combination use of depot and clozapine against the use of clozapine only. Similarly, we divided the whole observation period by different exposure types. The results showed that compare to clozapine use only, both combination use and depot use were associated with higher risk of all-cause, psychiatric and non-psychiatric hospitalization. We welcome and invite constructive comments and ideas from you.  

Early Career Awardee – Jennifer Lepock

Early Career Awardee Banner

P2 Visual Event-Related Potential Response Predicts Clinical Outcomes in Patients at Clinical High Risk for Psychosis - Transcript for SIRS 2025 Early Career Award 


Jennifer Lepock  


80%-90% of schizophrenia (SCZ) patients experience a period of less intense symptoms preceding psychosis with changes in mood, behavior, interests and thoughts (Addington & Heinssen, 2012) For example, whereas an individual with SCZ may have a fixed belief the FBI are spying on them, a Clinical High Risk (CHR) individual may have fleeting thoughts that they are being watched or followed by unknown persons, and still have insight that this may not be true. Our ability to predict SCZ based on CHR symptoms is still limited. A majority of CHR individuals will not go on to develop SCZ, but their psychiatric follow-up requires substantial time and cost for them and the health-care system, and carries risks of side effects and stigmatization. To avoid unnecessary treatment and target interventions to those most at risk, new tests are needed to predict which CHR patients are most likely to develop SCZ. Although only a minority of CHR patients develop psychosis, approximately half of those who do not do so continue to experience persistent symptoms. Moreover, approximately half of CHR patients who do not develop a psychotic disorder have poor social and/or occupational functioning at follow-up. 


Neurophysiological indices are a potential tool for enhancing our ability to predict outcomes in CHR patients. These indices offer the advantage of being objective and rater-independent . Cognitive event-related brain potentials (ERPs) are a type of neurophysiological index that uses electroencephalography to non-invasively record voltage changes at the scalp associated with cognitive events such as stimuli or responses. A number of ERP waveforms have been found to be reliably reduced in schizophrenia, contributing to our knowledge about its underlying neurocognitive pathophysiology.  

Some of these ERP waveforms have demonstrated promising predictive results in CHR patients. 

ERP measure that could plausibly contribute to prognostic algorithms in CHR populations is the N400 waveform.  

400 amplitudes are normally smaller (less negative) to meaningful stimuli that are more related to preceding context. This “N400 semantic priming effect” is attenuated in patients with schizophrenia, compared with control individuals. We have found CHR individuals to also have attenuated N400 semantic priming effects compared to controls, and these deficiencies predicted functioning at one and two year follow up. 


There is evidence that prediction effects can be seen even earlier when a stimulus fits what is predicted, during the stage of early visual processing of word form reflected by the P2, during the 175-300 ms time window after stimulus onset. 

In the present study, we aimed to examine whether the P2 amplitudes are abnormal in patients at clinical high risk (CHR). In CHR patients, P2 is an early indicator of using context to predict what comes next with regard to the orthographic form of predicted words, and deficits in this prediction may reflect increased risk for functional impairment. 

Early Career Awardee – Hsi Wei

Early Career Awardee Banner

Hsi Wei

00:00:02.333 --> 00:00:10.333 

Understand what happens in the brains of individuals experiencing psychosis related language difficulties down to a millisecond precision. 


00:00:10.383 --> 00:00:19.383 

Hi, I am Hsi Tiana Wei, a postdoctoral researcher at McGill University and Douglas Mental Health Institute, and I'm excited to share with you what we found. 


00:00:20.583 --> 00:00:26.583 

Schizophrenic patients struggle with daily communication in the form of flattened affect. 


00:00:26.483 --> 00:00:34.483 

Reduced and disorganized speech. To study speech, which is such a dynamic behavioral symptom. 


00:00:34.418 --> 00:00:43.418 

MEG is an excellent neuroimaging tool that allows us to record high precision of spatial temporal, spectral. 


00:00:43.833 --> 00:00:51.833 

And network level connectivity information. And these are all neuronal aspects that have shown deviations in schizophrenic patients. 


00:00:53.083 --> 00:01:04.083 

And importantly, without understanding the associations between these deviated neural dynamics with communicative symptoms and clinical symptoms in schizophrenic patients. 


00:01:04.618 --> 00:01:16.618 

The development of treatments focusing on neurochemical alterations using drugs or neural oscillatory modulations using non-invasive brain stimulations would be considerably limited. 


00:01:17.283 --> 00:01:29.283 

So to improve the understanding of these associations, the current study that we ran, recruiting We are recruiting 25 schizophrenic patients and 25 healthy controls. 


00:01:29.383 --> 00:01:39.383 

For three main domains of data. Including one session of MEG recording during a sensorimotor task so that we can characterize their neural dynamic. 


00:01:39.921 --> 00:01:47.921 

And a natural speech task where we will extract the linguistic and acoustic features using large language models. 


00:01:47.384 --> 00:02:02.384 

And a battery of clinical assessments. This is a rich data set that allowed us to look into the associations and interactions between neural dynamics, speech, and clinical symptoms in our patients and control groups. 


00:02:02.333 --> 00:02:07.333 

So we're not only looking at factors and features that differentiate patients from control. 


00:02:07.833 --> 00:02:18.833 

We're also looking into individual differences within each population group. So come to my presentation on April 1st at 5 p.m. In Regency Ballroom C. 


00:02:18.979 --> 00:02:26.979 

To hear more about what we found and discuss how this study can inform the development of neuromodulatory treatments for psychosis. Looking forward to seeing you there. 


Early Career Awardee – Deepa Purushothaman

Early Career Awardee Banner

Deepa Purushothaman

Hello everyone, 

My name is Deepa, and I am excited to introduce to you our team’s research. We are poster number M73: Atypical neural activation during live face gaze in First Episode Psychosis predicts Bureau of Labor Statistics classification. I am a post doc at Yale, and we are a collaborative project by the Hirsch lab and STEP program at Yale. So, let me take you to the first slide. 

So, have you ever wondered how we instinctively look at people’s face, especially eyes, when you are talking to them? So, eye gaze and facial expressions tell us a lot of things about people’s emotions, even when they are not talking. So that’s why eye gaze and facial expression processing is considered the core of social cognition. And we know that in Schizophrenia, these core social cognitive processes are impaired. But how do we test them? So, imagine I need to test the motor circuits necessary for riding a bike. So, these will not be completely engaged, the circuits will not be completely engaged unless I sit on a bike and start riding. Similarly, the social cognitive circuits will not be completely engaged unless I see another human being face to face and start communicating with him or her. So, seeing movie clips or seeing static images may help us in understanding the neurology but it will not completely engage the social cognitive circuit. So, this is a challenge we all face. This was our research question: How do we bring a real world social dynamic interaction into the lab? And this is something I am excited to discuss with you at SIRS. 

At Hirsch lab, we came across , we put forward or we discovered a unique paradigm which includes two people, natural facial expressions and live eye gaze. It’s essentially two-person neuroscience, and what we did was, we compared people with First Episode Psychosis from the STEP clinic with typically developing individuals who do not have any neurodevelopmental, neurologic or psychiatric conditions. And while they are doing the task, we did FNIRS. And we had some amazing findings , interesting findings. I am excited to talk to you about all those things at SIRS. But I can only say that these findings could have immense ecological validity, treatment implications and it could even be a biological marker. So, let’s meet at SIRS. 

Early Career Awardee – Deema Ali

Early Career Awardee Banner

Deema Ali

Slide 1 

Hi everyone, I’m Deema, a PhD student at the University of Galway. My research focuses on studying the role of FOXP1 transcription factor in schizophrenia risk and cognitive function across development.  


Slide 2 

Transcription factors are proteins that regulate gene expression by binding to specific regions of DNA.  

They are crucial for controlling when, where, and how genes are turned on or off, influencing important processes including brain development. 

One of the transcription factors we are interested in is Forkhead Box Protein P1, or FOXP1.
Which is expressed in both the developing and adult brain and is considered one of the key regulatory genes during neural development. 

Rare mutations in this gene are associated with an autosomal dominant neurodevelopmental disorder known as FOXP1 syndrome, which is characterized by intellectual disability, developmental delay, and speech and language delays. 

On the other hand, the recent schizophrenia-GWAS reported a number of genome-wide significant common variants within the FOXP1 gene. 

In this study, we aimed to investigate whether FOXP1-regulated genes contribute to schizophrenia risk, and if this contribution varies across different developmental stages. 


Slide 3 

To investigate this, we analyzed transcriptomic data generated from mouse and human models of FOXP1 loss-of-function across different developmental stages, including prenatal and postnatal periods.  

We used LD score regression analysis to determine whether FOXP1-regulated genes are enriched for schizophrenia heritability and we performed gene-set enrichment analysis to explore their overlap with schizophrenia-associated genes identified by single nuclei RNA-seq studies.  We also studied the role of FOXP1-regulated genes in synaptic functions and how FOXP1-SNPs affect the expression of its downstream genes.  


Slide 4 

Our main findings show that FOXP1-regulated genes are enriched for SCZ heritability, and this enrichment is stage-dependent. 

As we can see here that FOXP1-regulated genes show the highest enrichment for SCZ-associated genes during childhood and adolescence, while genes from the embryonic stage and newborn period show lower enrichment.  

We’ve also found that the enrichment for genes associated with cognitive functions is similar to that seen in schizophrenia.  

This highlights the importance of developmental timing in understanding genetic contributions to SCZ.  

Thanks for your attention and I would be happy to discuss more details at my poster number 82 


Wordpress Social Share Plugin powered by Ultimatelysocial


